Antibiotics for Diabetic Foot Infections: 12 Essential Things to Know
A diabetic foot wound does not always need antibiotics. An... Read more
DIABETIC FOOT SURGERY · CLINICAL CASES
Explore real osteomyelitis surgery cases showing how targeted bone surgery eradicates infection, preserves the foot, and often avoids major amputation.
Osteomyelitis surgery is guided by the extent of bone infection, soft-tissue involvement, perfusion and the possibility of preserving viable bone while achieving effective infection control.
Diabetic foot osteomyelitis requires careful assessment of infected bone and surrounding soft tissue. The cases below show how surgery can range from focused bone-preserving procedures to limited resection within a broader diabetic foot treatment plan and limb-salvage strategy.
For the complete collection organized by surgical approach, visit the Diabetic Foot Surgery – Clinical Cases hub.
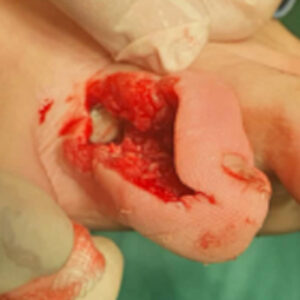
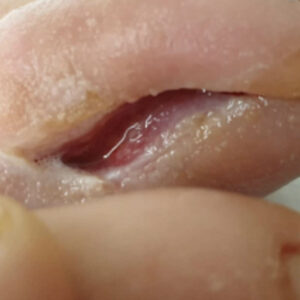
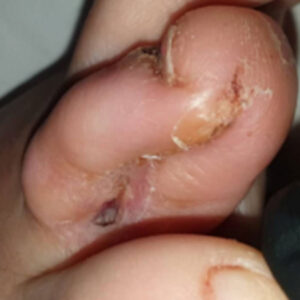
A 50-year-old woman with poorly controlled type 2 diabetes presented with osteomyelitis of the fifth toe. The infection had destroyed the phalanges, while the fifth metatarsal head remained viable. Preserving the soft-tissue envelope of the toe was essential to avoid a more proximal amputation.
Radical debridement and resection of the infected phalanges were performed while preserving the soft-tissue envelope of the fifth toe. The remaining soft tissues were used as a biological flap to cover and protect the preserved fifth metatarsal head, allowing healing by secondary intention.
The wound healed completely by secondary intention without further bone resection or toe amputation. Preservation of the soft-tissue envelope provided durable biological coverage of the fifth metatarsal head, maintaining foot contour and function.
This case illustrates that, even after complete phalangeal resection for osteomyelitis, preserving the soft-tissue envelope can avoid a more proximal amputation while preserving a functional foot.
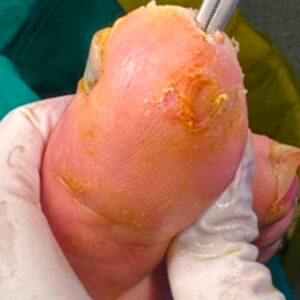
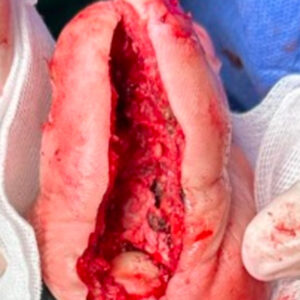
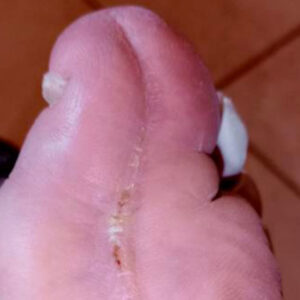
A 54-year-old man with diabetes presented with hallux osteomyelitis associated with a draining sinus tract. Infection involved the phalanges of the great toe, placing the hallux at risk of amputation.
Radical surgical debridement with resection of the infected phalanges was performed while preserving the soft-tissue envelope of the hallux. The wound was left to heal by secondary intention following complete eradication of the infected bone.
The wound healed completely by secondary intention within approximately 3 months, without the need for hallux amputation.
Complete eradication of osteomyelitis was achieved while preserving the great toe, maintaining its weight-bearing function and contribution to normal gait.
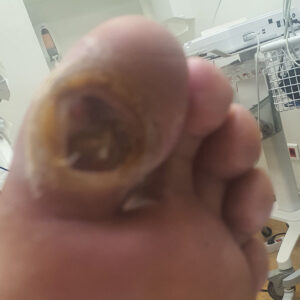
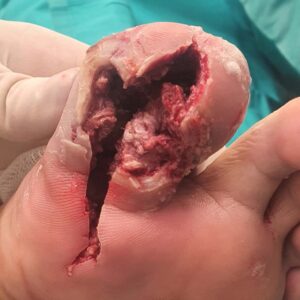
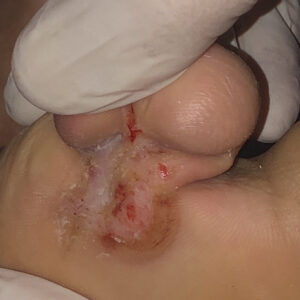
A 65-year-old man with diabetes presented with plantar hallux osteomyelitis and a deep plantar ulcer involving the phalanges of the great toe. The location of the ulcer on the weight-bearing surface made durable wound closure particularly challenging.
Radical surgical debridement and resection of the infected phalanges were performed while preserving the soft-tissue envelope of the hallux. The wound was managed by secondary intention until complete granulation and epithelialization were achieved.
The wound healed completely by secondary intention within approximately 3 months, without hallux amputation.
Despite the challenging plantar location, complete eradication of osteomyelitis was achieved while preserving the great toe, maintaining its weight-bearing function and contribution to normal gait.
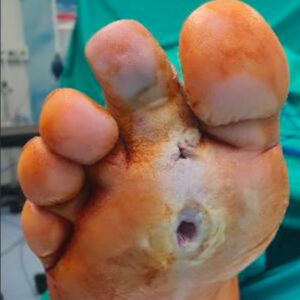
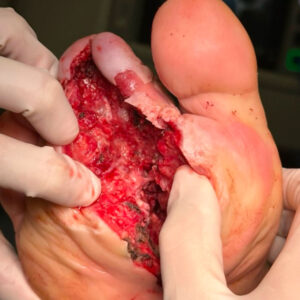
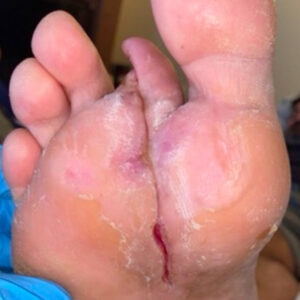
A 45-year-old man with type 2 diabetes presented with a plantar diabetic foot ulcer complicated by extensive osteomyelitis of the second ray, involving both the second metatarsal and the phalanges of the second toe.
Radical debridement with complete resection of the infected second metatarsal and second toe phalanges was performed until healthy, infection-free bone margins were achieved. The wound was managed with negative pressure wound therapy (NPWT) followed by secondary intention healing.
The wound healed completely within 50 days.
Despite complete resection of the infected second ray, the remaining forefoot was preserved, achieving infection eradication while maintaining a functional, weight-bearing foot.
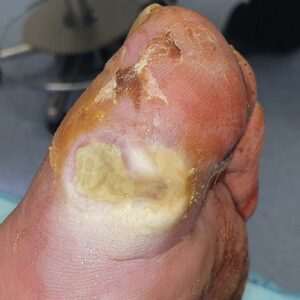
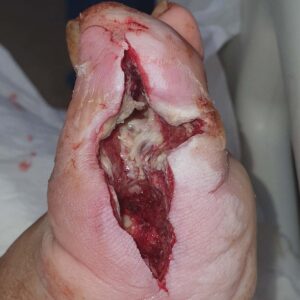
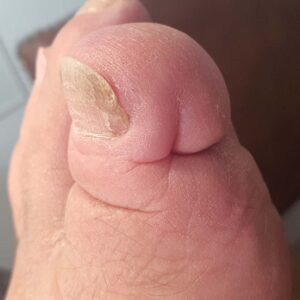
A 68-year-old man with type 2 diabetes presented with a diabetic foot ulcer complicated by osteomyelitis of the hallux phalanges. The infection extended throughout the phalanges, threatening exposure of the first metatarsal head and increasing the risk of a more proximal amputation if adequate soft-tissue coverage could not be maintained.
The infected hallux phalanges were resected until healthy, infection-free bone margins were achieved. Particular emphasis was placed on preserving the viable soft-tissue envelope of the hallux. Rather than sacrificing the entire toe, these preserved tissues were advanced and used as a biological flap to cover the first metatarsal head, providing durable soft-tissue coverage while allowing the wound to heal by secondary intention.
Complete wound healing was achieved within approximately 2.5 months.
By preserving and utilizing the hallux soft tissues as a biological flap, stable coverage of the first metatarsal head was achieved, infection was eradicated, and the biomechanical role of the first ray was preserved without the need for a more proximal amputation.
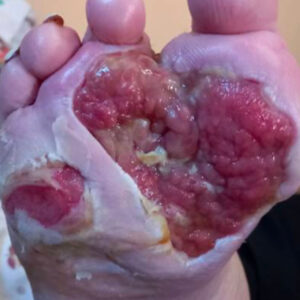
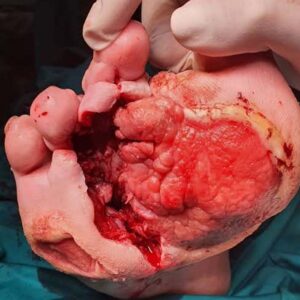
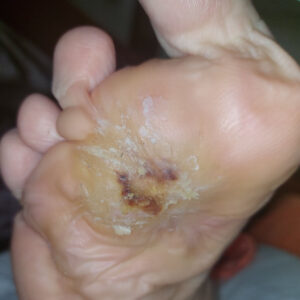
A 30-year-old woman with type 2 diabetes was referred from another hospital with extensive diabetic foot osteomyelitis involving the second and fourth metatarsals. Bone cultures revealed a multidrug-resistant organism, resistant to all available intravenous antibiotics. The infection was extensive and later recurred in the fourth metatarsal despite the initial procedure, making limb preservation particularly challenging.
A staged limb-salvage approach was undertaken. Radical debridement and resection of the infected second metatarsal were initially performed until healthy, infection-free bone margins were obtained. Following recurrence, the infected fourth metatarsal was also resected. Throughout treatment, every effort was made to preserve viable plantar soft tissues and maintain the structural integrity of the foot, allowing gradual healing by secondary intention while eradicating the infection.
Complete wound healing was achieved after approximately five months.
Despite multidrug-resistant osteomyelitis, multiple infected metatarsals, and disease recurrence, limb preservation was achieved. The patient regained independent ambulation using a customized therapeutic shoe, avoiding a major amputation while maintaining a functional, weight-bearing foot.
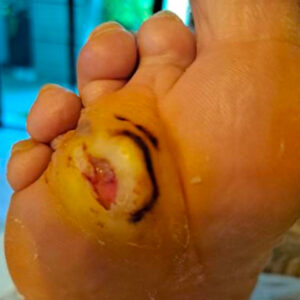
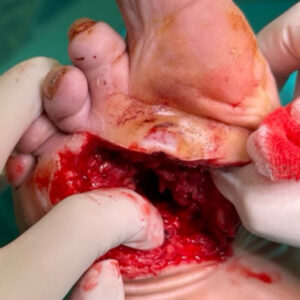
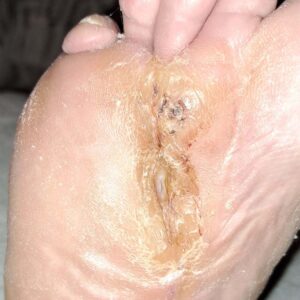
A 60-year-old woman with type 2 diabetes and peripheral arterial disease had previously undergone successful limb-sparing surgery by our team following lower-limb angioplasty for osteomyelitis of the second metatarsal. Two years later, she presented with a new plantar ulcer that had progressed to osteomyelitis involving the third metatarsal. The previous surgical scar, visible adjacent to the new lesion, demonstrates that this represented a new infectious episode rather than recurrence of the original infection.
Radical surgical debridement was performed with complete resection of the infected third metatarsal and the involved phalanges until healthy, bleeding bone margins were obtained. Viable plantar soft tissues were carefully preserved and mobilized to provide durable biological coverage of the resection cavity, maintaining forefoot stability and maximizing the potential for functional healing.
Complete wound healing was achieved in approximately three months.
Despite developing a second episode of metatarsal osteomyelitis two years after the initial limb-sparing procedure, the patient again avoided major amputation. Sequential conservative bone resections successfully eradicated infection while preserving a functional, weight-bearing foot, demonstrating that recurrent diabetic foot osteomyelitis can often be managed with repeat limb-salvage surgery rather than more proximal amputation.
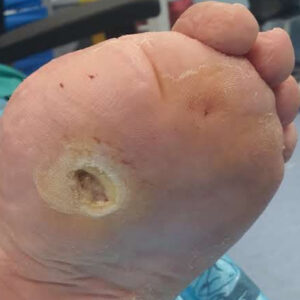
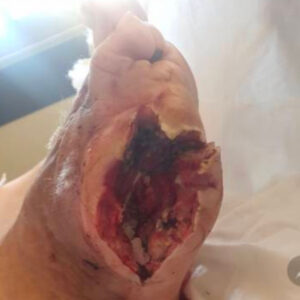
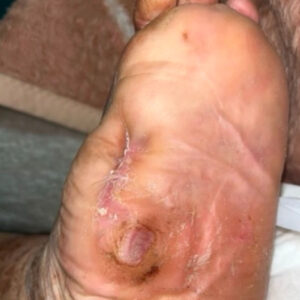
An elderly patient with type 2 diabetes was referred from another hospital following partial resection of the first metatarsal for diabetic foot osteomyelitis. Despite the initial surgery, persistent infection remained within the residual central portion of the first metatarsal, resulting in a chronic plantar wound with ongoing osteomyelitis.
Revision limb-sparing surgery was performed with complete excision of the residual infected first metatarsal until healthy, bleeding bone margins were achieved. Following meticulous debridement, negative pressure wound therapy (NPWT) was applied to promote granulation tissue formation, reduce wound volume, and prepare the wound for definitive healing.
Complete wound healing was achieved in approximately four months. This case illustrates that residual osteomyelitis after incomplete bone resection does not necessarily mandate major amputation. Careful revision surgery combined with NPWT can successfully eradicate persistent infection while preserving a functional, weight-bearing foot.
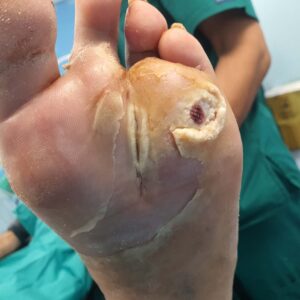
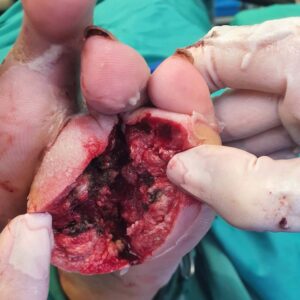
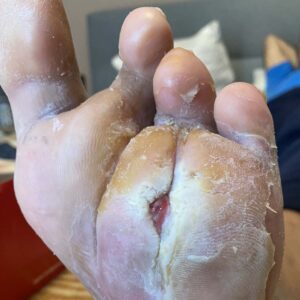
A 50-year-old man with type 2 diabetes, living abroad, presented with a chronic plantar ulcer of seven years’ duration. Despite prolonged conservative treatment, the wound failed to heal. Magnetic resonance imaging demonstrated osteomyelitis of the fourth metatarsal, identifying persistent bone infection as the underlying cause of the non-healing ulcer.
Limb-sparing surgery was performed with complete resection of the infected fourth metatarsal and the proximal phalanx of the fourth toe until healthy, bleeding bone margins were obtained. The surrounding viable plantar soft tissues were preserved to provide durable biological coverage of the surgical defect and facilitate healing by secondary intention.
Complete wound healing was achieved in approximately three months.
This case demonstrates that even a longstanding plantar ulcer of seven years can heal rapidly once the underlying osteomyelitis is surgically eradicated. Targeted bone resection eliminated the source of chronic infection, preserving a functional, weight-bearing foot while avoiding major amputation.
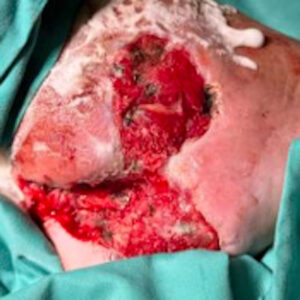
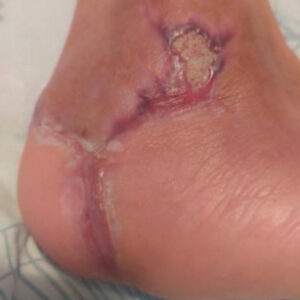
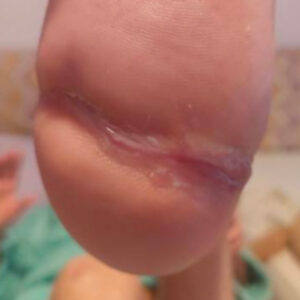
A 45-year-old woman with type 2 diabetes presented with calcaneal osteomyelitis after being advised at another hospital that major amputation was the only treatment option. The infection involved the calcaneus, threatening both limb preservation and independent ambulation.
Limb-sparing surgery was performed with meticulous excision of all infected calcaneal bone until healthy, bleeding bone margins were achieved. Every effort was made to preserve the surrounding viable heel soft tissues, maintaining the specialized plantar heel pad that is essential for durable weight-bearing and long-term foot function.
The wound healed completely in approximately 3.5 months, without the need for major amputation.
This case demonstrates that even calcaneal osteomyelitis—traditionally considered one of the most challenging diabetic foot infections—can often be successfully managed with aggressive bone-sparing surgery and preservation of the heel soft tissues. Careful eradication of infection, while maintaining the native weight-bearing heel pad, allowed limb salvage and preserved independent walking despite a previous recommendation for amputation.
Each case is presented to help advanced knowledge and improve patient outcomes.
NEED A CLINICAL EVALUATION?
Every diabetic foot problem requires individual assessment of infection, circulation, tissue viability and functional risk. Clinical cases are educational examples and do not replace an examination.
A diabetic foot wound does not always need antibiotics. An... Read more

A diabetic foot ulcer is an open wound or area... Read more

Diabetic Foot Assessment Before a Wound Develops Diabetic foot care... Read more